How the Anion Gap Measures in DKA
The anion gap is a lab-derived value that helps determine the cause of metabolic acidosis. In diabetic ketoacidosis, it is especially useful because it indicates the accumulation of acids that are not directly measured on a standard chemistry panel. This turns the anion gap a useful diagnostic tool for recognizing high anion gap metabolic acidosis.
An anion gap calculator estimates the difference between the major measured cations and anions in the blood. The result helps clinicians review serum chemistry data in the context of the patient’s acid-base balance. In DKA, the gap elevates as ketones build up and contribute unmeasured anions to the bloodstream.
Because DKA is an acidotic state, the body typically shows a low bicarbonate level along with an elevated anion gap. That pattern reflects ketone accumulation and a more general metabolic derangement. The anion gap does not diagnose DKA by itself, but it helps support the diagnosis and tracks how the condition is changing over time.
How to Work with an Anion Gap Calculator
An anion gap calculator relies on a few basic lab values from the electrolyte panel. You enter the serum sodium, serum chloride, and serum bicarbonate values, and the calculator applies the calculator formula to calculate the result.
The typical workflow is straightforward:
- Collect the latest serum sodium value. Obtain the serum chloride value. Record the serum bicarbonate value from the serum chemistry panel. Enter the values into the calculator. Examine the result alongside the rest of the laboratory results and clinical assessment.
This is useful because DKA evaluation hardly ever depends on one number alone. The anion gap is part of a wider lab interpretation process that includes the patient’s symptoms, glucose level, ketone testing, pH, and treatment response. A calculator speeds up the math, but interpretation still demands clinical judgment.
Many clinicians rely on the result as a quick screen for metabolic acidosis and as a marker of resolution of acidosis during treatment monitoring. As the underlying ketoacidosis improves, the anion gap should trend toward normal and eventually show anion gap closure.
Anion Gap Formula and Normal Ranges
The traditional anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
With this equation, the calculator estimates the relationship between measured ions in the blood. Sodium is the key measured cation, while chloride and bicarbonate are the principal measured anions included in the equation. Any additional acids in the blood are often represented indirectly as unmeasured anions.
The normal anion gap range changes a bit depending on the laboratory method and the reference range used by that lab. That variation is why it is important to read the number in context rather than rely on a single universal cutoff. A mildly different result may still be normal if the lab’s reference interval differs.
In practice, the anion gap should be considered with the rest of the electrolytes and with awareness of albumin correction. Albumin is a negatively charged protein that affects the gap, so lower albumin can make the gap appear falsely low or normal. That is one reason a raw value may not tell the full story.
Why the Anion Gap Is Increased in DKA
In DKA, reduced insulin leads to increased fat breakdown and formation of ketones, particularly acetoacetate and beta-hydroxybutyrate. These acids accumulate in the blood as unmeasured anions, which increases the anion gap and leads to ketoacidosis.
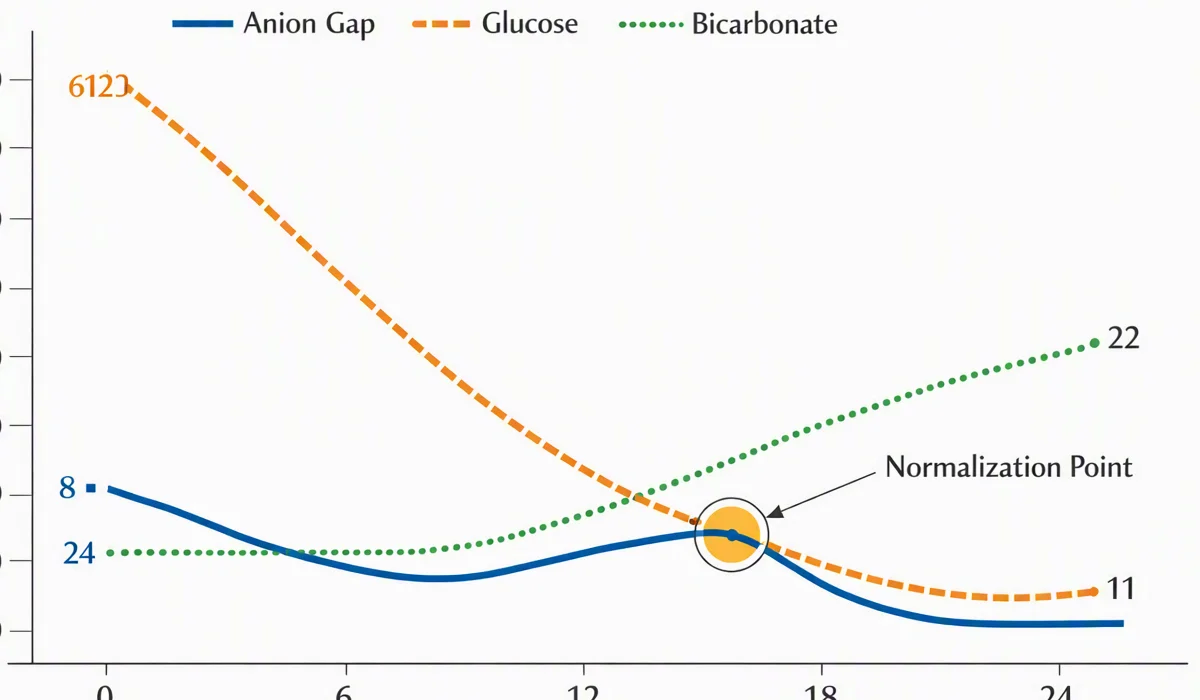
The process is a straightforward disturbance in acid-base balance. As ketones accumulate, they consume bicarbonate, lowering the bicarbonate level and producing a metabolic acidosis with a high anion gap. This pattern is a recognizable hallmark of DKA and helps separate it from other forms of acidosis.
Beta-hydroxybutyrate is commonly the dominant ketone in severe DKA, so the degree of ketosis may be greater than a urine ketone test suggests. That is why the anion gap and direct ketone testing are supportive. Together, they describe the patient’s acid burden more fully than either test alone.
Correcting the Anion Gap for Albumin
Albumin plays a major role in the measured anion gap because it is a major unmeasured anion in blood. When albumin is low, the anion gap may be too low. This is why albumin correction is often recommended, especially when the clinical picture suggests acidosis but the raw gap seems less concerning than expected.
Hypoalbuminemia can occur in many hospitalized patients and can mask a true high-gap process. In that setting, a corrected anion gap gives a more accurate picture of the patient’s metabolic state. The corrected value helps avoid missing DKA or failing to recognize the degree of acid accumulation.
Although formulas for albumin correction can be slightly different, the goal is the same: correct the gap based on the measured serum albumin so the value better reflects the true acid burden. This matters because a normal-looking gap can be misleading normal AG adult range if albumin is low. In DKA workups, the corrected value can improve lab interpretation and support more accurate treatment monitoring.
Other Labs to Review Alongside the Anion Gap
The anion gap is just one component of the DKA workup. A careful evaluation also covers blood glucose, ketone measurement, and acid-base testing. These studies aid in confirming the diagnosis and inform management.
An arterial blood gas or venous blood gas can provide the pH and bicarbonate level, which indicate how severe the acidemia is. While venous testing is often adequate in many settings, the choice is based on the clinical context. Either way, the pH helps define the acidotic state and contributes to the differential diagnosis.
Beta-hydroxybutyrate is especially useful because it directly indicates ketone burden. It can verify ketone accumulation even when other markers are less clear. Blood glucose is also essential, but a normal or only mildly elevated glucose does not rule out DKA, especially in euglycemic presentations.
Reviewing these findings together builds a more complete picture of the metabolic derangement. The anion gap, blood gas, glucose, and ketones should be viewed as a group rather than as isolated laboratory results.
How the Anion Gap Changes During DKA Treatment
Care of DKA typically includes insulin administration and fluid replacement. As insulin suppresses ketone production and fluids support circulation and renal clearance, the anion gap should progressively fall. This trend is one of the clearest signs that treatment is effective.
During treatment monitoring, the clinician looks for anion gap closure, which suggests that the major ketoacid burden is resolving. The gap may normalize before the bicarbonate fully recovers, so it is important to look at the entire pattern rather than one value alone.
Electrolyte monitoring is vital during this phase. Potassium, sodium, chloride, and bicarbonate can shift quickly as therapy progresses. IV fluids and insulin can also affect the apparent acid-base profile, so serial labs are needed to verify true improvement rather than a temporary lab shift.
As treatment continues, the goal is not only to improve glucose but also to correct the underlying acidosis. The anion gap helps indicate whether the ketoacid production has ended and whether the body is moving toward a stable acid-base balance.
Common Pitfalls and Interpretation Errors
A typical error is not recognizing a combined acid-base disorder. A patient with DKA may also have emesis, problems with respiratory compensation, or a separate metabolic process that modifies the expected pattern. In those cases, the anion gap may not show the full picture by itself.
Testing error is another concern. A single incorrect sodium, chloride, or bicarbonate result can distort the calculated gap and lead to incorrect conclusions. If the number does not fit the clinical picture, it is wise to repeat testing and assess the full electrolyte panel.
Hyperchloremic metabolic acidosis can occur during or after DKA treatment, especially after large volumes of chloride-containing fluids. This can lower the bicarbonate while the anion gap normalizes, making the metabolic picture look unclear. In that setting, the persistent acidosis may be due to chloride rather than ongoing ketone production.
Albumin also is important here. If albumin is low and not accounted for, the gap may appear falsely reassuring. Careful lab interpretation requires awareness of the corrected value, the clinical assessment, and the treatment timeline.
When a Normal Anion Gap Does Not Exclude DKA
A normal anion gap does not definitively rule out DKA. One important example is euglycemic DKA, where the blood glucose may be normal or only mildly elevated despite active ketoacidosis. This can happen in certain medication contexts or with reduced carbohydrate intake, and it requires a high index of suspicion.
Another reason the gap may seem normal is that β-hydroxybutyrate can remain elevated even when other markers are less dramatic. In early or partially treated disease, the anion gap may also begin to improve before the full metabolic picture resolves. That is why clinical evaluation is so important.
If the patient still has symptoms and there is persistent acidosis on blood gas testing, DKA can still be present even when the gap is not clearly elevated. In that setting, the differential diagnosis should include DKA, mixed disorders, and other causes of acidosis. The anion gap is valuable, but it is not a standalone rule-out test.
FAQ
What does the anion gap mean in diabetic ketoacidosis?
The anion gap in diabetic ketoacidosis is a calculated lab value that helps identify increased anion gap metabolic acidosis. The gap rises because ketones accumulate as unmeasured negative ions, decreasing bicarbonate and enlarging the gap. It is used to aid diagnosis and monitor response to treatment.
How do you calculate the anion gap from lab values?
Use this anion gap calculator or use the anion gap equation: sodium minus the sum of chloride and bicarbonate. The needed values are serum sodium, blood chloride, and serum bicarbonate. The result should be read in the context of the rest of the serum chemistry and clinical findings.
What is considered a normal anion gap range in adults?
The expected anion gap range depends on the laboratory’s reference range and testing method. Since ranges can differ, the best approach is to compare the result with the lab’s stated normal limits rather than relying on one universal number. Albumin level can also change what appears normal.
What is the reason for correcting the anion gap for albumin?
The anion gap is corrected for albumin because low albumin can make the gap appear falsely low or normal. In low albumin, the measured value may underestimate the degree of acidosis. Albumin correction helps produce a more accurate adjusted anion gap for lab interpretation.
Is diabetic ketoacidosis possible with a normal anion gap?
Yes, it can. Euglycemic DKA, early treatment, low albumin, or a mixed acid-base disorder can make the gap appear normal even when DKA is still present. If symptoms, ketones, pH, and bicarbonate suggest ongoing disease, the diagnosis should still be considered despite a normal gap.