What Is the Meaning of the Anion Gap?
The anion gap is a test-derived value that helps clinicians evaluate electrolytes and detect an acid-base disorder. It is calculated from common blood chemistry results, especially sodium, chloride, and bicarbonate. Because it indicates the balance of measured ions in the blood, the anion gap can act as a useful diagnostic clue during metabolic acidosis evaluation.
In simple terms, the anion gap contrasts the positively charged ions and negatively charged ions reported on an electrolyte panel. Most commonly, the calculation uses serum sodium as the main measured cation, then deducts serum chloride and serum bicarbonate. The resulting anion gap result helps differentiate between different causes of acidosis and supports further lab interpretation.
An anion gap calculator speeds up this process by applying the standard equation automatically. That is helpful because the value itself is only part of the picture; the real value comes from understanding what the number indicates about electrolyte balance and the likely cause of the patient’s symptoms or test result.
Anion Gap Equation and Input Values
The classic anion gap formula reads:
Anion gap = sodium - (chloride + bicarbonate)
Most calculator tools ask for three inputs: sodium, chloride, and bicarbonate. These values typically are obtained from a standard blood panel or similar blood test. Once entered, the calculator calculates the anion gap and supports a more informed clinical assessment.
Certain systems may include potassium in a different version of the equation, but the most frequently used bedside and online approach relies on sodium, chloride, and bicarbonate. This makes the calculation useful for quick blood chemistry review and routine lab interpretation.
To use an anion gap calculator properly, make sure the numbers are from the same sample and expressed in compatible units, typically mEq/L. If the lab reports values in another format, adjust them before calculating to avoid an incorrect result.
How to Calculate the Anion Gap Step-by-Step
To calculate anion gap manually, start out with the three values from the lab panel. Then apply the formula in order. A careful step-by-step approach reduces errors and improves the accuracy of the test result.
Step 1: Find the serum sodium value.
Step 2: Locate the serum chloride value.
Step 3: Identify the serum bicarbonate value.
Step 4: Add chloride and bicarbonate together.
Step 5: Deduct that total from sodium.
Here is a simple calculation example:
If the test values are sodium 140 mEq/L, chloride 104 mEq/L, and bicarbonate 24 mEq/L, the calculation is:
140 - (104 + 24) = 140 - 128 = 12 mEq/L
In this example, the anion gap is 12 mEq/L, which is often within a typical reference range depending on the laboratory. This kind of hands-on example is useful because it shows how the numbers on a blood test become a useful diagnostic clue.
When using an online calculator, the same steps happen right away. Still, understanding the arithmetic helps you confirm the output and connect it to the broader picture of electrolyte balance and acid-base disorder.
Normal Anion Gap Range and Reference Values
The normal range for the anion gap depends on the laboratory and the measurement method used. There is not one universal reference range, which is why clinicians assess the result in context rather than using one fixed cutoff.
Many labs report a normal anion gap in a range that is approximately the low teens, but the exact value can shift with assay differences and laboratory variation. Because of that, it is best to compare the test result with the specific reference interval shown on the blood test report.
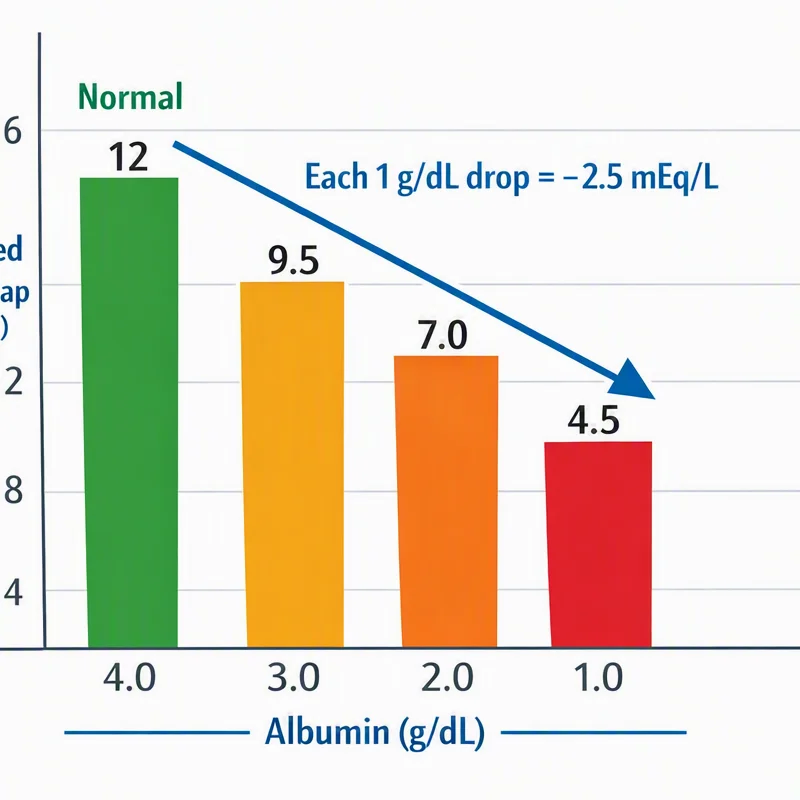
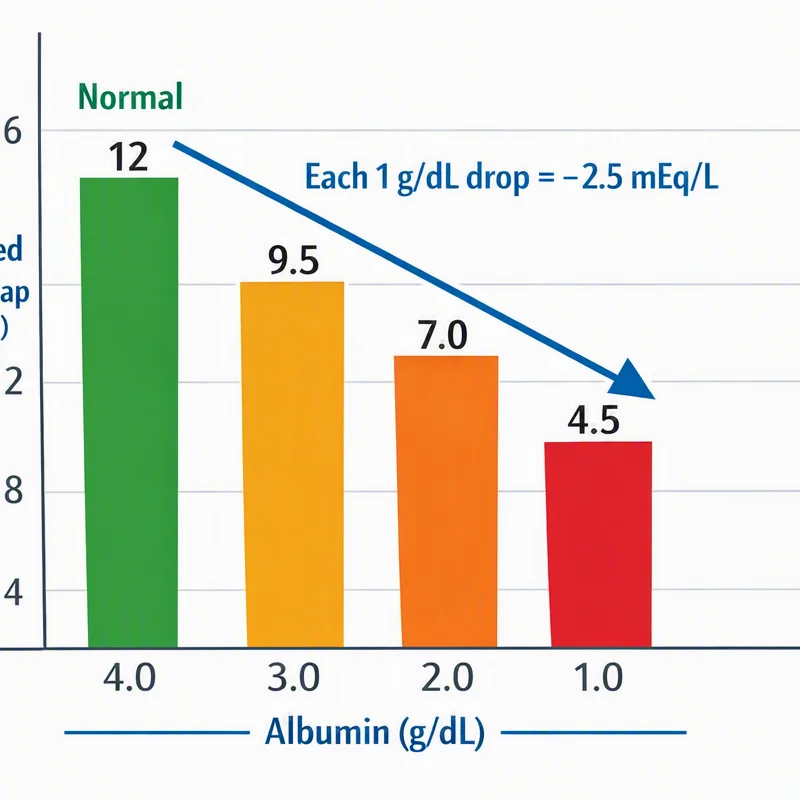
Albumin also matters. Since albumin is an unmeasured anion, low albumin can lower the apparent gap and make a high-gap problem harder to detect. That is one reason a result should always be interpreted using both the numeric value and the surrounding clinical context.
If the value sits near the upper end of the normal reference range, it may still warrant attention in a patient with symptoms or other lab abnormalities. A borderline test result can provide a useful diagnostic clue even when it does not clearly fall outside the range.
How a Raised Anion Gap Can Suggest
A raised anion gap frequently suggests metabolic acidosis from the build-up of uncounted acids in the blood. This finding is sometimes called high gap acidosis, and it can be an useful signal that additional testing is needed.
Frequent causes include lactic acidosis, ketoacidosis, and toxic alcohol ingestion. Every one of these conditions alters the blood chemistry in a different way, but all can increase the anion gap by adding acid or acid-like substances that are not directly counted in the standard panel.
A buildup of lactic acid may occur when tissues do not receive enough oxygen or when severe illness disrupts normal metabolism. Ketoacidosis can occur in uncontrolled diabetes, prolonged fasting, or other states of excess fat breakdown. Toxic alcohol ingestion is another serious cause that can create dangerous acid-base changes and requires urgent evaluation.
When the anion gap is elevated, the number alone does not reveal the cause. Instead, it acts as a key clue that prompts a broader review of symptoms, vital signs, medication history, and additional laboratory results. That is why the value is most useful as part of a structured overall assessment.
What a Normal Anion Gap May Indicate
A result that is normal or close to normal does not exclude acid-base issues. In fact, normal anion gap acidosis may still point to clinically important disease. This pattern is often called non-anion gap metabolic acidosis or non-gap acidosis.

Frequent causes are diarrhea, renal tubular acidosis, and hyperchloremia. In these situations, https://anion-gap-calculation.com/acid-base-disorders/hagma.html bicarbonate is lost, but chloride rises to keep electrical balance, so the calculated gap may fall within the normal reference range.
Diarrhea can lead to loss of bicarbonate from the gastrointestinal tract. Renal tubular acidosis impairs the kidneys’ ability to process acid or bicarbonate properly. Hyperchloremia, which means an elevated chloride level, may indicate the body’s compensation for bicarbonate loss or another underlying condition.
Because of this, a normal gap should not be read as “everything is fine.” It merely points to a different pattern of acid-base disorder. Careful electrolyte interpretation and review of the broader blood test results are still essential.
Serum albumin Correction and Modified Anion Gap
Albumin adjustment is important because decreased albumin can make the reported gap seem lower than it truly really is. When hypoalbuminemia is present, the raw number may miss the degree of unmeasured negative ions in the blood. In those cases, a corrected anion gap can offer a more reliable estimate.
Serum albumin has a negative charge and plays a major role to the body’s unmeasured anion pool. If albumin is reduced, the gap may fall even if an acid load is occurring. This is why many clinicians use an albumin-adjusted approach, especially when reviewing unexplained acidosis.
The exact correction method can differ by institution, but the principle is the same: revise the result based on the albumin level so the final value better matches the patient’s actual acid-base status. This can help prevent a missed diagnosis in someone whose lab test shows low protein levels.
Total protein may also put in context the result, although it is not used directly in the standard equation. Alongside albumin, it can support a more thorough view of the patient’s biochemical state and strengthen the quality of lab interpretation.
How to Use the Anion Gap Calculator Safely
An anion gap calculator is a useful tool, but it should be used as part of thorough electrolyte interpretation. The result is only meaningful when you consider the clinical context, the patient’s complaints, and the rest of the blood chemistry.
Before relying on the result, confirm that the inputs come from the identical electrolyte panel and that units are consistent. If the sodium, chloride, or bicarbonate values are stale or inconsistent, the calculated number may be deceptive. Good lab interpretation depends on accurate, recent data.
It is also important to avoid reading too much into a single test result. A normal result does not exclude serious illness, and an elevated result does not identify the cause by itself. The calculator is best understood as a support tool for medical disclaimer purposes: it can help shape thinking, but it does not replace professional judgment or formal diagnosis.
If the result suggests metabolic acidosis or a different concerning pattern, additional evaluation may be needed. That may include repeat labs, blood gas analysis, review of medications or toxins, and assessment for infection, kidney problems, or other underlying causes. In short, use the calculator as part of a wider clinical assessment, not as a isolated answer.
Frequently Asked Questions
What is the anion gap formula?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate: anion gap = sodium - (chloride + bicarbonate). This formula is the core of most calculator tools and is used to support acid-base interpretation.
What is a normal anion gap value?
A normal anion gap value depends on the lab’s reference range and measurement method. Many laboratories report a normal range in the low teens, but laboratory variation is frequent, so the report’s listed interval should be used for interpretation.
How do you work out the anion gap from sodium, chloride, and bicarbonate?
In order to calculate the anion gap, combine chloride and bicarbonate together, then deduct that total from sodium. For example, if sodium is 140 mEq/L, chloride is 104 mEq/L, and bicarbonate is 24 mEq/L, the result is 12 mEq/L. An anion gap calculator calculates it automatically.
Why does low albumin affect the anion gap?
Albumin is a key unmeasured anion in the blood. When hypoalbuminemia is present, the measured gap may seem lower than expected, which is why albumin correction is sometimes needed. A corrected anion gap offers a better estimate of the real acid-base picture.
What can cause a high anion gap?
A high anion gap is often associated with metabolic acidosis from conditions such as lactic acidosis, ketoacidosis, and toxic alcohol ingestion. These causes increase unmeasured acids in the blood and can suggest a serious problem that needs urgent evaluation.