What the Anion Gap Measures
The anion gap is a practical way to measure the distribution of electrically charged particles in the blood, especially when checking acid-base balance. It is calculated from standard serum electrolytes and helps clinicians calculate anion gap numbers as part of a more complete metabolic acidosis evaluation. In typical situations, the calculation uses sodium, chloride, and bicarbonate from an electrolyte panel.
This number is not a true measurement of acids. Instead of that, it estimates the amount of unmeasured anions in the blood. Those unmeasured substances can increase in metabolic acidosis, making the anion gap a valuable diagnostic tool for detecting unexpected acidosis. It is especially important when looking at serum bicarbonate level changes that may indicate an acid-base problem even before the full picture is obvious.
The anion gap is often used to help interpret lab results when the cause of acidosis is not obvious at once. A high value can point to extra acids in the blood, while a normal value can suggest other forms of acid loss or replacement. Because the calculation is based on everyday serum electrolytes, it is widely available and easy to track over time.
Why Albumin Affects the Anion Gap
Albumin is one of the major protein bound anions in plasma, so it has a important effect on the measured anion gap. When albumin is low, the gap may seem smaller than it really is because fewer negatively charged proteins are present to contribute to the total. This is why hypoalbuminemia can hide a true acid-base problem.
To account for this, clinicians use albumin correction to calculate a corrected anion gap. This adjusted value is often called the albumin adjusted anion gap. It helps correct for albumin so that the result better reflects the actual presence of unmeasured anions.
This correction matters because a normal-looking anion gap may not be truly normal when albumin is reduced. In patients with low serum albumin level, the uncorrected number can downplay the severity of metabolic acidosis. That means albumin adjustment improves the utility of the result for clinical interpretation and may improve diagnostic accuracy.
In short, albumin changes the anion gap because it is a major contributor to the negative charge in plasma. If albumin falls, the measured gap often falls too, even when the underlying acid-base disorder has not improved.
How to Work With an Anion Gap Calculator
An Anion Gap Calculator makes easier the step of calculating and refining the gap. To use it, you usually enter the values for sodium, chloride, bicarbonate, and albumin. The calculator then runs the anion gap formula and, when needed, the albumin adjustment on its own.
The basic workflow is simple:
- Add the sodium value from the lab report. Input chloride and bicarbonate values. Add the albumin value if albumin correction is needed. Check the calculated anion gap and the corrected anion gap. Match the result with the reference range used by the lab.
This process allows clinicians and learners interpret lab results quickly, especially when evaluating acid base status. It also minimizes arithmetic mistakes and aids faster recognition of electrolyte imbalance patterns. For practical use, the calculator serves as a fast diagnostic tool that can help screen for hidden acidosis.
When reviewing the result, remember that the calculator is only a single part of the overall picture. The numbers must still be interpreted in context with the patient’s symptoms, history, and other laboratory findings.
Anion Gap with Albumin Formula and Computation Steps
The standard anion gap formula is:
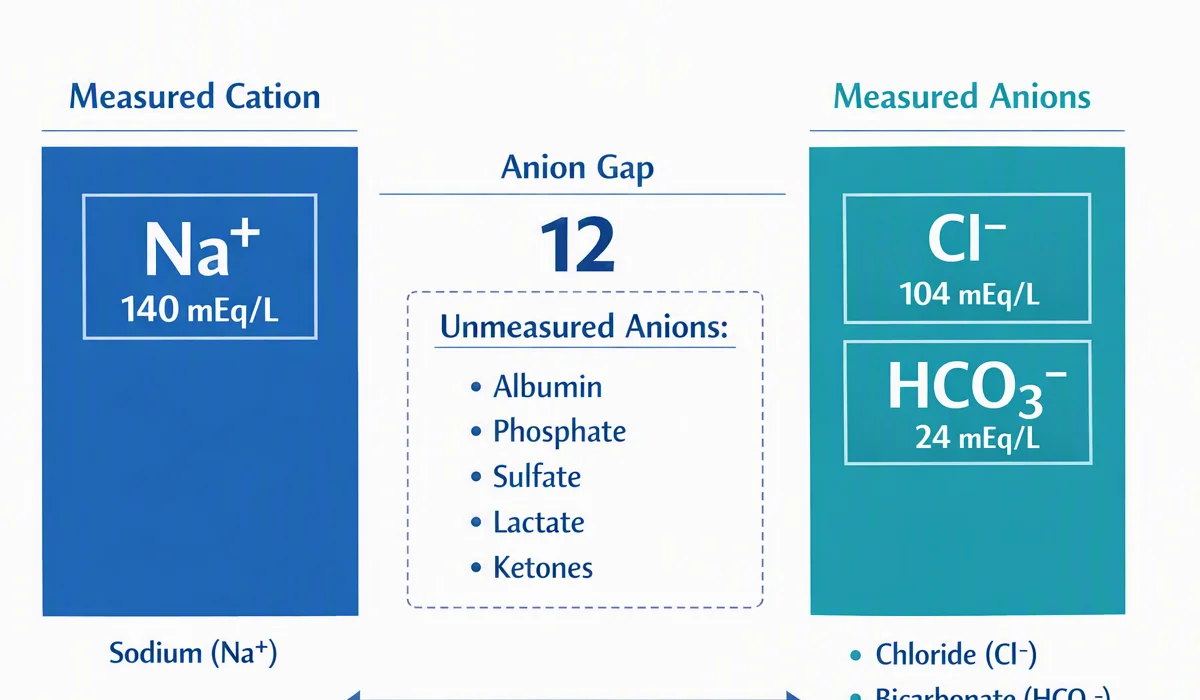
Anion gap = sodium − (chloride + bicarbonate)
This value is generally reported in mmol/L. The exact reference range can vary by laboratory method, but the calculation itself is straightforward and broadly applied.
To apply albumin correction formula, a commonly used approach is to add a correction factor based on the patient’s albumin level. A common method adds approximately 2.5 mmol/L to the anion gap for every 1 g/dL decrease in albumin below normal. The specific method may vary by institution, so the laboratory reference range and local practice should always be checked.
Here is a practical step-by-step method:
- Compute the initial anion gap using sodium, chloride, and bicarbonate. Check the serum albumin level. When albumin is low, use the albumin correction. Review the albumin adjusted anion gap in mmol/L. Match both the raw and corrected values with the expected reference range.
Calculation example: If sodium is 140 mmol/L, chloride is 104 mmol/L, and bicarbonate is 20 mmol/L, the uncorrected anion gap is 16 mmol/L. If albumin is low, the corrected anion gap may be higher after adjustment, which could change the interpretation from borderline to clearly abnormal. This is why the calculator is helpful for both teaching and bedside clinical interpretation.
The purpose is not only to produce a number. It is to improve the acid-base analysis more accurate by accounting for changes in protein bound anions that alter the baseline.
Explaining High, Normal, and Low Anion Gap Findings
A raised result often points to high anion gap metabolic acidosis, which means extra acids or unmeasured anions are building up. This pattern usually warrants a focused search for the reason, especially if the bicarbonate is low and symptoms match the pattern.
A normal result does not always eliminate a anion gap clinical significance problem. Normal anion gap metabolic acidosis can occur when bicarbonate is lost and replaced by chloride, leaving the calculated gap unchanged. In these cases, the acid-base disturbance is real, but the gap is not elevated. That is why the full lab pattern matters so much in clinical interpretation.
A low anion gap is less common but still significant. It can occur with low albumin, lab variation, or unusual positively charged substances. A low value should not be ignored, especially if the patient has other signs of electrolyte imbalance or a broader acid-base problem.
In practice, the interpretation depends on the relationship between the gap, bicarbonate, chloride, and albumin. This is where the Anion Gap Calculator becomes very useful because it helps tell apart a truly normal value from one that only appears normal because of hypoalbuminemia.
Key interpretation points include:
- Elevated gap: consider extra acids and metabolic acidosis. Within-range gap: think about bicarbonate loss or chloride replacement. Decreased gap: check albumin, method issues, and unusual lab patterns.
Common Causes of Abnormal Anion Gap
Several conditions are closely linked to abnormal anion gap values. Some of them elevate the gap because they increase acidity in the blood, while others decrease it indirectly by changing the protein or electrolyte levels.
Lactic acidosis is a typical cause of high anion gap metabolic acidosis. When tissues are underperfused or oxygen delivery is limited, lactate accumulates and the gap rises. This is commonly encountered in severe illness and is a major reason clinicians use the anion gap as part of metabolic acidosis evaluation.
Ketoacidosis is another common cause. In diabetic, alcoholic, or starvation states, ketone bodies add to the pool of unmeasured anions, increasing the gap. A high value in this setting often supports the diagnosis when the rest of the data align.
Renal failure can also increase the gap because the kidneys fail to clear acid efficiently. As acids accumulate, the bicarbonate falls and the gap may increase. This makes the anion gap a useful clue in chronic or acute kidney dysfunction.
Toxic alcohols are another important cause to consider. Certain ingestions produce organic acids that elevate the gap and can cause dangerous acid-base imbalances. In such cases, the anion gap may provide an early warning signal that requires urgent attention.
Other causes can include severe tissue hypoperfusion, sepsis, or mixed toxic exposures. Because multiple processes can overlap, the calculator should be used as part of a broader clinical interpretation rather than as a standalone answer.
When to Correct the Anion Gap for Albumin
Albumin correction is especially important when hypoalbuminemia is present. In patients with decreased albumin, the uncorrected anion gap may underestimate the degree of acid accumulation, resulting in missed or delayed recognition of metabolic acidosis.
This adjustment is particularly helpful in critical illness, where albumin often decreases and acid-base disorders are frequent. In this setting, relying on the raw number alone can limit diagnostic accuracy. The adjusted value gives a more accurate view of the true acid-base status and can help identify a hidden gap that would otherwise be overlooked.
It is also helpful when the clinical picture suggests acidosis but the measured gap looks normal. In such cases, albumin adjustment can help account for the discrepancy and improve acid-base disorders assessment. This is one reason the calculator is often used to screen for hidden acidosis.
Cases where albumin correction is often helpful include:
high anion gap evaluation- Reduced serum albumin level Critical illness Ambiguous acid-base balance abnormalities Possible unexpected acidosis with a borderline gap
In short, if albumin is low, the corrected value is usually more useful clinically than the uncorrected one.
Limitations and Clinical Caveats
Although the anion gap is valuable, it has significant limitations. Multiple labs may use distinct measurement methods, which means lab variability can affect the result. A value that is normal in one setting may not be normal in another, so the local reference interval matters.
Another major caveat is the chance of a mixed acid-base disorder. A patient may have more than one process at the same time, such as a high-gap acidosis plus a metabolic alkalosis. In that situation, the bicarbonate and anion gap may not behave in a simple way, and careful analysis is required.
Likewise, a broader electrolyte imbalance can skew the interpretation. Changes in sodium, chloride, or bicarbonate can shift the number even when the underlying clinical condition is complex. That is why the gap should always be interpreted alongside the full chemistry panel and clinical context.
Other caveats include unusual proteins, analytical differences, and the fact that albumin correction is an estimate rather than a perfect measurement. The adjusted result is informative, but it is still only one part of a full acid-base evaluation.
Best practice is to use the calculator as a guide, then confirm the pattern against symptoms, history, and related laboratory findings. That approach improves confidence in the final clinical interpretation.
Frequently Asked Questions
What is an anion gap calculator used for?
An Anion Gap Calculator is used to determine and interpret the anion gap from common serum electrolytes. It helps clinicians evaluate acid-base balance, identify metabolic acidosis, and detect a possible hidden acid load when the routine lab pattern is not obvious.
How do you correct the anion gap for albumin?
To correct for albumin, first calculate the raw gap using sodium, chloride, and bicarbonate. Then apply an albumin correction factor based on the patient’s serum albumin level. Because low albumin lowers the measured gap, the adjustment produces a more reliable corrected anion gap.
What may be a standard anion gap interval?
The anion gap normal range varies by the laboratory’s approach and normal range. That is why it is important to assess the result using the local laboratory reference range rather than using one universal number. The calculator helps you compare the result with the appropriate interval.
Why does low albumin reduce the anion gap?
Albumin is a primary source of negative charge in the blood because it contains protein bound anions. When albumin is low, there are less negative charges contributing to the gap, so the measured value drops. This is why hypoalbuminemia can make the gap appear falsely low or low.
What conditions cause a high anion gap?
Typical causes of a high gap include lactic acidosis, ketotic acidosis, renal insufficiency, and toxic alcohols. These conditions add to unmeasured anions and often produce anion gap metabolic acidosis. The exact cause should be worked out by the full clinical picture and supporting labs.