Understanding the Anion Gap?
The anion gap is a derived value used to help interpret serum electrolytes and judge acid-base balance. It reflects the difference between the main measured cations and anions in the blood, most often using sodium, chloride, and bicarbonate. In simple terms, it helps clinicians recognize whether there are unmeasured acids or other changes affecting the anion difference.
The standard anion gap formula is usually written as:
Anion gap = sodium - (chloride + bicarbonate)
Some versions add potassium, but the simplified formula above is most common in routine serum chemistry and is especially useful for quick bedside clinical interpretation. A normal reference range changes by laboratory method, which is why the exact number should always be read in context rather than in isolation.
The key idea is electroneutrality: the body keeps total positive and negative charges balanced. If one measured ion changes, another often shifts in the opposite direction to preserve balance. That is why the anion gap is not just a number; it reflects underlying physiology and electrolyte balance.
What Is the Chloride Shift?
The chloride shift is an ion exchange reaction that allows red blood cells move carbon dioxide. As carbon dioxide enters red blood cells, it is turned into bicarbonate. To maintain electrical balance, bicarbonate exits of the cell while chloride passes in. This exchange supports efficient gas transport and supports normal physiology.
This process is also sometimes described as a “chloride-bicarbonate exchange.” It is central to how the body handles CO2 during circulation and supports normal buffering. Because bicarbonate is involved in this transport, the chloride shift directly affects measured concentrations of bicarbonate concentration and chloride concentration, especially when analyzing lab values in blood gas analysis.
Although the chloride shift is a normal process of red blood cells, the term can also be used more broadly in acid-base discussions to explain situations where chloride rises as bicarbonate falls. In that setting, the shift becomes important for understanding hyperchloremic acidosis and changes in the calculated gap.
In what way the Chloride Shift Alters Anion Gap Calculations
The anion gap formula helps make the impact of the chloride shift more straightforward to see. Since the formula subtracts both chloride and bicarbonate from sodium, any change that lowers bicarbonate and raises chloride can keep the calculated gap relatively stable. This pattern is important because it reflects electroneutrality rather than a large buildup of unmeasured anions.
Below is the basic logic:
- If bicarbonate loss occurs, the anion gap calculation tends to rise only if unmeasured anions replace the lost bicarbonate. If chloride increase occurs at the same time bicarbonate falls, the calculated gap may remain normal. The net effect is often a preserved calculated gap despite clear evidence of metabolic acidosis.
This is why the chloride shift is very important in acid-base interpretation. A drop in bicarbonate does not automatically mean a high anion gap. If chloride rises enough to offset that bicarbonate loss, the result is often a normal calculated gap with a specific acid-base pattern.
For example, if sodium stays stable while bicarbonate decreases and chloride rises by a similar amount, the formula may produce little change in the calculated gap. That pattern suggests a normal anion gap metabolic acidosis rather than a high anion gap metabolic acidosis. In other words, the anion difference has not widened because chloride is filling the space left by bicarbonate.
This relationship is a practical reminder that the anion gap is a diagnostic aid, not a standalone diagnosis. It must be interpreted alongside symptoms, serum chemistry, and blood gas results.
Does the Chloride Shift Lead to a High or Normal Anion Gap?
Usually, the chloride shift is associated with a normal anion gap metabolic acidosis, not a elevated anion gap. That is because the rise in chloride replaces the bicarbonate that was lost, preserving acid-base balance in the calculation. The patient may still have metabolic acidosis, but the anion gap stays normal because the retained negative charge is carried by chloride.
This pattern is commonly called elevated chloride-associated acidosis or chloride-associated acidosis. In this situation, chloride goes up, bicarbonate goes down, and the calculated gap remains within the expected range. The blood is still acidotic, but the mechanism is different from conditions that create a high gap.
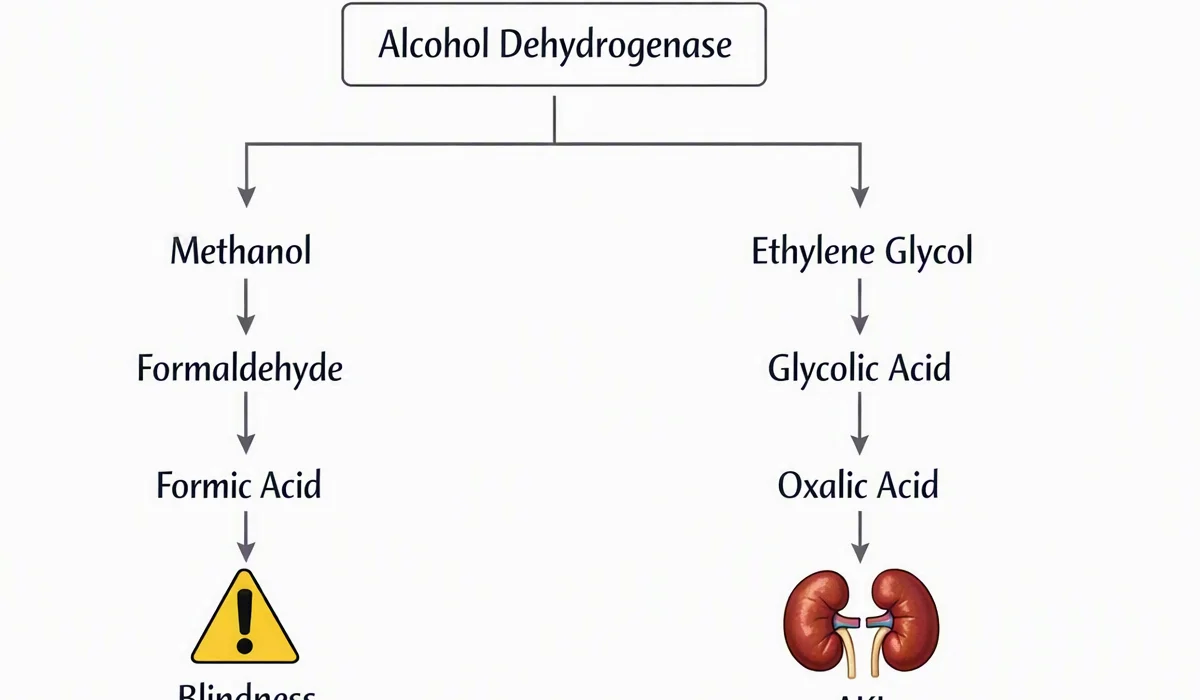
On the other hand, a high anion gap metabolic acidosis occurs when unmeasured acids accumulate, such as lactate, ketones, or toxins. In those cases, bicarbonate falls, but chloride does not rise enough to replace it. The gap increases because extra unmeasured anions are present.
So the answer depends on the mechanism:
- Chloride replacement during the shift usually supports a normal anion gap. Accumulation of unmeasured acids usually produces a high anion gap.
Knowing that distinction improves acid-base analysis and helps separate a chloride-driven process from other forms of metabolic acidosis.
When to Apply an Anion Gap Calculator
An Anion Gap Calculator is helpful any time you have serum values for serum sodium, serum chloride, and serum bicarbonate and want a rapid review of the calculated gap. It is particularly important when evaluating a patient with possible metabolic acidosis, because it can quickly show whether the numbers fit a chloride-driven pattern or a high-gap process.
You can use the calculator when:
- Assessing routine lab values in a chemistry panel Evaluating suspected acid-base disorders Contrasting findings with an arterial blood gas Determining whether hyperchloremia may explain the bicarbonate drop
Because the reference range differs by lab methodology, the calculator should be anion gap clinical significance used as a tool rather than a strict rule. It is a diagnostic aid that aids clinical judgment. In practice, the best use is to combine the calculated gap with the overall serum chemistry picture, symptoms, and blood gas analysis.
The calculator is especially valuable when the clinical picture is ambiguous. For example, a patient may have low bicarbonate, but if chloride is also elevated, the anion gap may remain normal. That result points toward a normal gap process rather than a hidden accumulation of acids.
Frequent Medical Situations In Which Chloride Shift Is Important
A number of clinical scenarios are tightly linked to chloride shift and associated acid-base profiles. The most common are diarrhea, renal tubular acidosis, and saline infusion. Each one can lower bicarbonate while raising chloride, creating a normal anion gap acidosis profile.
With diarrhea, bicarbonate is lost from the gastrointestinal pathway. The body may retain chloride to maintain electrical balance, leading to hyperchloremia and a non-gap result. This is a textbook profile of bicarbonate wasting without extra unmeasured acids.
In renal tubular acidosis, the kidneys fail to manage acid and bicarbonate properly. Depending on the subtype, this can cause a normal gap metabolic acidosis with higher chloride. The core issue is reduced acid excretion or bicarbonate reabsorption, not necessarily an increase in unmeasured acids.
After high volumes of saline infusion, the chloride load can increase relative to bicarbonate. This may lower bicarbonate and create a pattern of hyperchloremic acidosis. The result is often a lower bicarbonate concentration with a maintained calculated gap.
These situations show why acid-base disorders should be assessed in context. The very same low bicarbonate value can indicate different things depending on whether chloride is increased, whether the gap is normal, and whether there is indication of a high gap process.
How to Interpret Results Together with Blood Gas Values
The anion gap should never be interpreted alone. It is most reliable when combined with an arterial blood gas and other measures from blood gas analysis. In combination, these data show whether a patient has true acidemia, HAGMA toxic causes compensation, or a mixed disorder.
Start with pH. If pH is low, the patient is acidemic. Next check pCO2 to see whether a respiratory process is contributing. Low pCO2 often reflects respiratory compensation for metabolic acidosis, while high pCO2 may indicate respiratory acidosis or a mixed disorder.
Then assess bicarbonate and the calculated gap. If bicarbonate is low and pH is low, the process is likely metabolic acidosis. If chloride is high at the same time, the anion gap may remain normal. That pattern supports a chloride-driven process rather than a high gap disorder.
Base excess is also useful. A negative base excess usually supports a metabolic acid load or bicarbonate deficit. If base excess is reduced while chloride is elevated, that finding fits with hyperchloremic metabolic acidosis. The overall picture may show metabolic compensation if pCO2 has fallen appropriately.
A simple interpretation approach is: pH first, pCO2 second, bicarbonate third, then calculate the gap and compare it with chloride. This sequence often reveals whether the problem is a chloride shift, bicarbonate loss, or a high-gap acid accumulation.
That systematic method improves acid-base interpretation and reduces the chance of missing a mixed disturbance.
Frequently Asked Questions
What is the chloride shift in simple terms?
The chloride shift is the transfer of chloride into red blood cells as bicarbonate leaves, helping the cells transport carbon dioxide effectively. It is a routine exchange process that helps maintain electroneutrality and assists buffering.
Does chloride shift increase or decrease the anion gap?
By itself, the chloride shift usually does not create a high anion gap. When chloride rises as bicarbonate falls, the calculated gap often stays normal. That is why this pattern is commonly associated with normal anion gap metabolic acidosis or hyperchloremia.
Why does bicarbonate drop when chloride rises?
Bicarbonate can drop when the body expels base or when bicarbonate is exchanged for chloride to preserve electroneutrality. In the blood, this often means a lower bicarbonate level paired with a higher chloride level. The result is a maintained calculated gap even though metabolic acidosis may still be present.
Can a normal anion gap still mean acidosis?
Yes. A normal anion gap can still occur in acidosis, especially in normal anion gap metabolic acidosis. In that case, bicarbonate is reduced, but chloride rises enough to keep the calculated gap within range. This is common in diarrhea, renal tubular acidosis, and after saline infusion.
When should I use an Anion Gap Calculator?
Use an Anion Gap Calculator whenever you have serum sodium, serum chloride, and serum bicarbonate and want to easily assess the anion gap. It is especially helpful when evaluating suspected acid-base problems, comparing results with an arterial blood gas, or deciding whether the pattern suggests a chloride-driven disorder or a high anion gap metabolic acidosis.