Lactic acidosis usually raises the anion gap because lactate accumulates as an unmeasured anion during metabolic acidosis. In plain terms, when the body makes too much lactic acid or cannot remove it fast enough, hydrogen ions rise and serum bicarbonate drops, which changes the electrolyte pattern seen on a blood chemistry panel. An Anion Gap Calculator can help you estimate whether the result is elevated, but the number only is useful when you interpret it alongside lactate level, albumin, and blood gas findings.
What Is the Anion Gap?
The anion gap is a calculated value that aids estimate the balance between measured plus and anionic charges in the blood. It is usually derived from serum electrolytes, especially sodium, chloride, and serum bicarbonate. Although it sounds like a direct measurement, the anion gap is actually a useful calculation that helps detect hidden acids or other unmeasured anions.
In basic terms, the calculation matches sodium against chloride and bicarbonate. When bicarbonate drops because of an acid load, the anion gap often goes up if the missing bicarbonate is replaced by other anions that are not directly measured. This is why the anion gap is such a useful diagnostic clue in acid-base interpretation.
Clinically, the anion gap is part of acid-base balance. It aids separate different causes of metabolic acidosis and can point toward conditions such as lactic acidosis, ketoacidosis, or toxin exposure. Because the result depends on lab values from the serum chemistry, even minor changes in sodium, chloride, or bicarbonate can change the interpretation.
What Is Lactic Acidosis?
Lactic acidosis is a type of metabolic acidosis caused by excess lactate and lactic acid in the circulation. Lactate is produced when cell metabolism shifts toward oxygen-free metabolism, meaning the body is making energy without enough oxygen supply for normal oxygen-dependent processes. get more info This frequently occurs during reduced blood flow to tissues, severe illness, or other states that impair oxygen delivery.
When lactate accumulates, it reflects a metabolic derangement rather than a single disease by itself. The underlying cause may be sepsis, shock, hypoxia, extreme exertion, seizures, liver dysfunction, or medication-related effects. In each case, the core issue is that cells cannot metabolize fuel normally, so lactate builds up and the buffer system becomes overwhelmed.
Lactic acidosis is medically important because it often indicates serious illness. A rising lactate measurement may be an initial sign that the body is under strain and needs immediate assessment. The acid-base disorder may progress quickly, so trends matter as much as the measured value.
In what way does Lactic Acidosis Increase the Anion Gap
Elevated lactate levels increases the Anion Gap because lactate is an unmeasured anion. As lactic acid dissociates, it gives off hydrogen ions and forms lactate. The hydrogen ions are handled, often by bicarbonate, which reduces serum bicarbonate on the blood chemistry panel. At the same time, lactate persists in circulation as a negatively charged particle that is not directly included in the standard Anion Gap calculation.
This leads to a high Anion Gap metabolic acidosis. The “gap” widens because measured bicarbonate decreases while unmeasured anions accumulate. In other words, the body is trading bicarbonate for acid, and the extra acid shows up obliquely through the calculation.
This mechanism is why lactic acidosis is so strongly linked to elevated Anion Gap findings. The Anion Gap does not measure lactate directly, but it often mirrors the metabolic consequence of lactate accumulation. That makes it a useful clue, not a standalone diagnosis.
A practical way to think about it is this: more lactate means more acid load, more hydrogen ions, and more consumption of bicarbonate. The result is a pattern that often points toward high Anion Gap metabolic acidosis. However, the size of the gap does not always reflect the severity of illness, so the full clinical picture matters.
Applying an Anion Gap Calculator in Clinical Context
An Anion Gap Calculator is a simple way to estimate whether the anion gap is elevated from a standard set of electrolytes. It typically relies on sodium, chloride, and serum bicarbonate from a blood chemistry panel. For many patients, this is the starting step in recognizing a possible acid-base disorder.
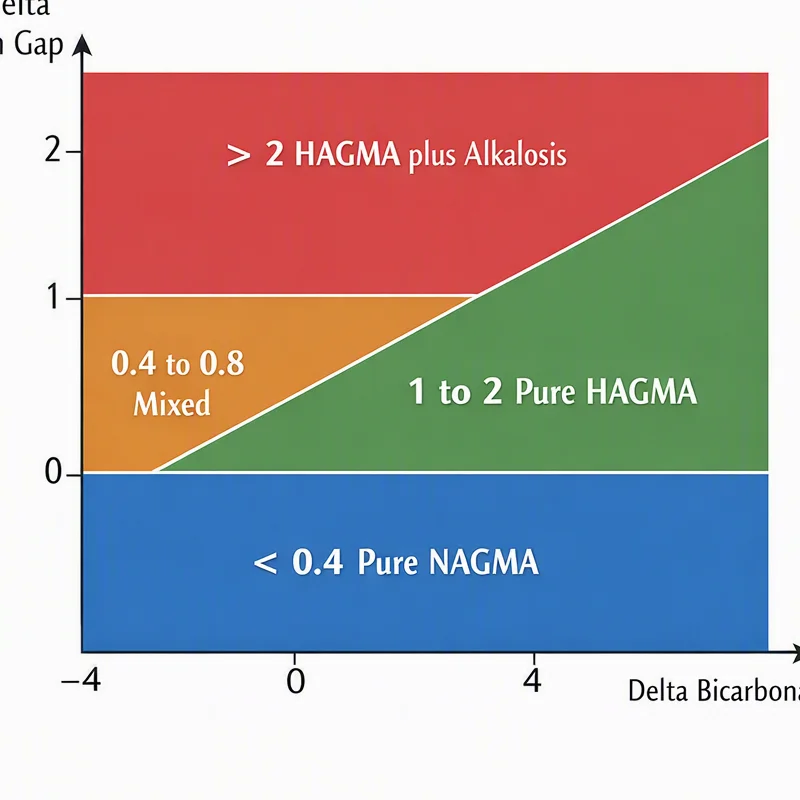
That said, the raw number should not be interpreted alone. Albumin has a significant effect on the anion gap because it is an major unmeasured anion. When albumin is low, the measured gap may look less impressive than it truly is. This is why an albumin-corrected anion gap can be more reliable in patients with low albumin, especially in critical illness.
Applying the calculator alongside serum chemistry and blood gas results helps you put together the dots. For example, if the anion gap is elevated and serum bicarbonate is low, that supports metabolic acidosis. If the lactate level is also elevated, lactic acidosis becomes a strong part of the differential diagnosis. If the albumin is low, correction may show an even more significant acid-base abnormality than the uncorrected value suggests.
In practice, the calculator is especially helpful when it is used as part of overall acid-base interpretation. It should guide next steps, not replace them. The most important question is not just whether the anion gap is high, but why it is high and whether the patient needs immediate care.
Common Causes of Elevated Lactate and High Anion Gap
Various conditions can raise lactate and lead to an high anion gap. The primary are situations of reduced tissue oxygenation or poor perfusion. Sepsis is a common cause because infection can cause tissue hypoperfusion, inflammation, and metabolic stress. Shock from blood loss, heart failure, or other causes can do the same.
Hypoxia can also promote lactate formation because cells shift to anaerobic metabolism when oxygen delivery is inadequate. Even when blood oxygen looks normal, poor circulation can prevent oxygen from reaching tissues effectively. This mismatch between oxygen delivery and cellular needs is a classic driver of lactate accumulation.
Medications can also contribute. Some drugs interfere with mitochondrial function or change how the body clears lactate. When reviewing an elevated anion gap, it is important to consider medications as part of the underlying cause. That keeps the differential diagnosis broad and helps avoid missing a reversible trigger.
Other causes of high anion gap metabolic acidosis can occur alongside lactic acidosis. For that reason, the presence of lactate does not automatically end the evaluation. Clinicians often look for additional acid-base derangement, renal dysfunction, toxin exposure, or other metabolic problems that could be contributing.
How to Understand an Elevated Anion Gap
An elevated anion gap is a signal, not a conclusive result. The first step is to find out whether the pattern fits an acid base disorder such as metabolic acidosis. If serum bicarbonate is low and the anion gap is high, the result strongly suggests excess unmeasured acids. If the situation is unclear, a blood gas can help clarify the acid-base balance.
Both ABG and venous blood gas testing can be valuable, depending on the situation. A blood gas provides pH and carbon dioxide information that helps determine whether there is compensation or a mixed disorder. In many settings, a venous blood gas gives enough data for initial evaluation, while an arterial sample may be used when oxygenation or ventilation needs more detailed evaluation.
Interpretation improves when you check the anion gap with the lactate level. If lactate is elevated, that supports lactic acidosis as the cause of the gap. If the gap is high but lactate is normal, other diagnoses become more likely. That is why acid-base interpretation should always include both the laboratory pattern and the clinical picture.
The compensatory response also counts. The body may try to lower carbon dioxide through faster breathing to partially offset metabolic acidosis. This does not fix the underlying problem, but it can shape the blood gas pattern. Reviewing these pieces together gives a clearer view of the patient’s acid-base balance.
When to Seek Prompt Attention
Elevated lactate can be a marker of a severe condition, and particular warning signs should not be ignored. Mental confusion, shortness of breath, extreme weakness, chest discomfort, or hypotension may indicate that the body is not receiving sufficient oxygen or circulation. These signs can accompany sepsis, shock, or other dangerous illnesses that require right away care.
If someone has signs of worsening illness along with an elevated anion gap or high lactate level, they need urgent evaluation. A delay can allow acid-base derangement to worsen and may increase the risk of organ dysfunction. Because the underlying cause may be easily reversible, timely evaluation matters.
Seek emergency care if symptoms are abrupt, intense, or associated with altered mental status. Mental confusion in particular is an important alerting sign because it may reflect reduced brain perfusion, serious metabolic imbalance, or both. Shortness of breath and low blood pressure are also warning signs that should be checked right away.
In short, do not delay for the calculator result alone to decide. If the person appears very ill, the safest step is to seek urgent care. Lab values are useful, but the clinical significance comes from the full picture.
FAQ: High Lactate and Anion Gap
Why does lactic acidosis cause a high anion gap?
Elevated lactate causes a high anion gap because lactic acid splits into hydrogen ions and lactate. The hydrogen ions are absorbed, which lowers serum bicarbonate, while lactate remains as an unmeasured anion. That combination increases the anion gap and creates a pattern of high anion gap metabolic acidosis.
Can you have lactic acidosis with a normal anion gap?
Yes, absolutely, it can happen, especially at first or if another factor lowers the observed gap. Low albumin can hide an elevated anion gap, which is why the albumin-corrected anion gap is helpful. A normal gap does not completely eliminate lactate accumulation, so the lactate level and blood gas still are important.
How large is the anion gap in lactic acidosis?
The anion gap can range broadly depending on the intensity of illness, the amount of lactate accumulation, and the patient’s albumin level. No single value exists that establishes lactic acidosis. The key is whether the gap is raised relative to the lab’s reference range and whether the other findings suggest metabolic acidosis.
Does albumin affect the anion gap in lactic acidosis?
Yes. Albumin is one of the primary unmeasured anions, so low albumin can make the anion gap look reduced than it really is. In patients with low albumin, an albumin-corrected anion gap gives a more reliable estimate of the true acid-base abnormality. This is especially important in serious illness.
What tests confirm lactic acidosis when the anion gap is elevated?
The most direct test is a lactate level, which helps show lactate accumulation. Clinicians also review serum bicarbonate, sodium, chloride, albumin, and a blood gas to evaluate acid-base balance. A blood gas or venous blood gas can demonstrate the pH and compensation pattern, while the blood chemistry panel helps identify the elevated anion gap and inform the differential diagnosis.