If you want to calculate anion gap values accurately, the key is grasping how the anion gap is formed from routine electrolytes and why low albumin can mask a clinically relevant abnormality. An Anion Gap Calculator can speed up the math, but the real advantage comes from knowing how to read the result in acid-base analysis.
What Is the Anion Gap?
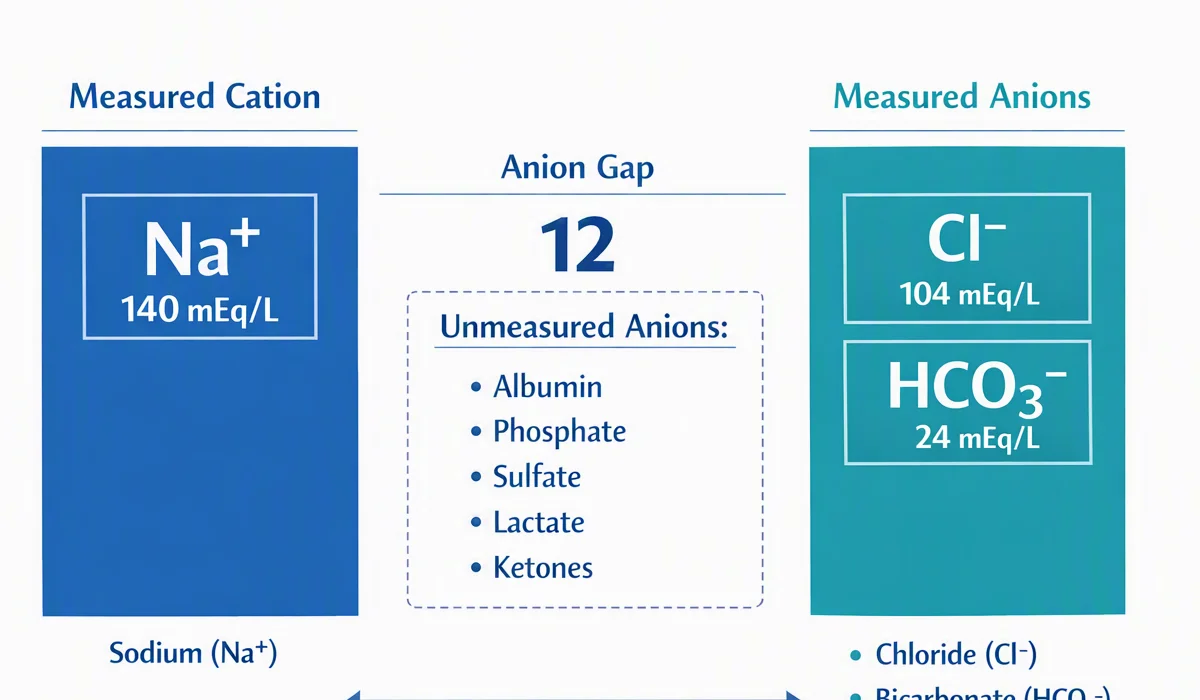
The anion gap is a estimated number that helps measure the difference between measured positive and negative charges in the blood. It is usually calculated from common lab values on a blood test, especially sodium, chloride, and bicarbonate. In many cases, potassium may also be included depending on the formula being used.
Clinically, the anion gap is a useful diagnostic aid in evaluating an acid-base disorder. It helps identify whether an unexplained metabolic acidosis may be present and whether the cause is likely to be due to unmeasured acids, changes in proteins, or shifts in serum electrolytes. The calculation is part of a larger metabolic panel or basic metabolic panel, which provides a picture of key lab values.
The concept is basic: blood contains positively charged ions and negatively charged ions. The measured ions do not account for everything present, so the “gap” reflects unmeasured components. A normal result falls within a reference range that varies slightly by laboratory and by whether potassium is included in the formula.
In what way the Anion Gap Calculator Works
An anion gap calculator is built to automate the calculation of the gap using the lab values entered from a basic metabolic panel or similar electrolyte test. Most often, the calculator uses sodium, chloride, and serum bicarbonate. Certain versions also accept potassium, which slightly alters the formula.
At its core, the calculator uses an anion gap formula such as:
Anion gap = Sodium − (Chloride + Bicarbonate)
If potassium is included, the formula changes to:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
This calculated measurement can help limit math errors and allow quicker review when reviewing serum electrolytes. The calculator may also help highlight values that are outside the normal range, which is especially helpful when assessing possible electrolyte imbalance or an acid-base disorder.
However, the calculator is only as useful as the data supplied. A missing or inaccurate lab value can lead to incorrect interpretation. That is why the clinical significance of the number depends on the full lab context, especially the bicarbonate level, the patient’s albumin status, and any evidence of acid-base disturbance.
Adjusted Anion Gap: Overview and Formula
The adjusted anion gap is the anion gap corrected for the effect of albumin, which is the chief negative protein in blood. Because albumin has a strong effect on the normal anion gap, a low albumin level can make the gap appear misleadingly normal. That is where albumin correction becomes important.
The purpose of this correction is to better reflect true acid-base status. In a patient with hypoalbuminemia, the measured gap may miss the presence of unmeasured acids. The adjusted value is sometimes called the corrected anion gap.
A common correction formula is:
Corrected anion gap = Measured anion gap + 2.5 × (4.0 − serum albumin in g/dL)
This is an albumin adjustment factor used to estimate how much the low albumin is lowering the result. Different references may use slightly different factors, but the goal is the same: anion gap clinical significance adjust for albumin so the interpretation is more accurate.
Why does this matter? Albumin is one of the major negatively charged proteins in plasma. When it drops, the body may preserve electroneutrality by increasing chloride or bicarbonate-related shifts, and the anion gap can look deceptively normal. Using the effective value improves interpretation in acid-base analysis.
Stepwise Guide: How to Calculate Effective Anion Gap
To determine the effective anion gap, follow a clear stepwise approach using the available lab values. This is the practical method clinicians use when reviewing serum electrolytes and deciding whether the patient has a hidden high-gap disorder.
Step 1: Review the lab values from the blood test.
- Sodium Chloride Bicarbonate Serum albumin
Step 2: Work out the measured anion gap using the standard formula.
Anion gap = Sodium − (Chloride + Bicarbonate)
Step 3: Contrast the result with the laboratory reference range.
Step 4: When albumin is low, apply the calculation formula for albumin adjustment.
Corrected anion gap = Measured anion gap + 2.5 × (4.0 − serum albumin)
Step 5: Evaluate the corrected anion gap in the context of the patient’s acid-base state.
Below is a worked example. Assume the labs show:
- Sodium: 140 Chloride: 104 Bicarbonate: 18 Serum albumin: 2.0 g/dL
Measured anion gap:
140 − (104 + 18) = 18
Albumin correction:
Corrected anion gap = 18 + 2.5 × (4.0 − 2.0)
Corrected anion gap = 18 + 5 = 23
Here, the measured result is elevated, and the albumin-adjusted value is even higher. This suggests a more significant underlying problem than the raw number alone would show.
When using an Anion Gap Calculator, be sure to check whether the tool includes albumin correction. Certain calculators provide only the standard result, while others display both the measured and corrected values. In clinical practice, the adjusted result can be especially helpful when the serum albumin is low.
How Albumin Changes the Anion Gap
Hypoalbuminemia changes the anion gap because albumin holds a minus charge and functions as a major unmeasured anion in plasma. When albumin falls, the body’s charge balance changes, often reducing the observed anion gap even if a true acid-base problem exists.
This explains why albumin matters so much in acid-base balance. In people with low albumin, a normal anion gap may not actually rule out a high-gap process. Without adjustment, the lab pattern can look less abnormal than it truly is.
Multiple physiologic factors contribute to this effect:
- Albumin is a major source of unmeasured negative charge. Shifts in protein binding can alter the distribution of ions. The body may compensate by shifting chloride or bicarbonate.
Because of this, clinicians often rely on albumin correction when the clinical picture suggests an acid-base disorder but the basic calculation seems borderline. In that setting, the corrected number gives a better estimate of the true gap.
How to Interpret the Result
Understanding the anion gap is not just about judging whether the number is high or normal. It is about linking the measurement to the overall acid–base picture. A high anion gap often points to the presence of unmeasured acids and can be seen in metabolic acidosis.
Common high-gap processes include lactic acidosis and ketoacidosis. In both settings, acid accumulates and bicarbonate is consumed, which elevates the gap. If the corrected value is elevated, the finding becomes even more important because low albumin may have masked the severity of the problem.
Conversely, a normal result does not always mean the problem is resolved. A normal anion gap can still occur in metabolic acidosis, particularly when bicarbonate falls and chloride rises in a way that keeps the calculated difference. This is why the result should be interpreted alongside pH, bicarbonate, and the rest of the clinical assessment.
Practical interpretation tips:
- A high corrected gap supports a high-gap metabolic acidosis. A normal measured gap with low albumin may still hide an elevated corrected gap. Trend changes can be more informative than a single value. Always compare the result with the patient’s symptoms and other lab values.
The main goal of gap calculation is to support thoughtful clinical interpretation, not to replace it. The number is a tool for identifying patterns in serum electrolytes and for identifying whether extra workup is needed.
Common Causes of a Elevated or Low Anion Gap
Many conditions can alter the gap higher or down. A increased anion gap often reflects acid buildup, while a low result may point to a difference in proteins, lab methods, or higher-than-normal chloride. Understanding the cause helps link the number to the patient’s overall status.
Frequent causes of a high anion gap include:
- Lactic acidosis, due to tissue hypoperfusion, sepsis, or other causes of impaired oxygen delivery Ketoacidosis, including diabetic ketoacidosis, starvation ketoacidosis, or alcohol-related ketosis Renal failure, where acid excretion is reduced and unmeasured acids accumulate Toxic alcohols, such as methanol or ethylene glycol, which can generate acid metabolites
Common causes of a low or apparently normal gap include:
- Hyperchloremia, which can offset bicarbonate loss and keep the calculation from rising Marked hypoalbuminemia, which lowers the measured value Lab variation or measurement issues that affect sodium, chloride, or bicarbonate Increased unmeasured cations in certain uncommon settings
Some disorders, such as renal failure, may also produce mixed findings depending on the stage and the patient’s fluid status. Likewise, toxic alcohols often need urgent recognition because the gap may rise before other symptoms become obvious.
One more important cause of an unusual low or altered result is multiple myeloma. This condition can affect blood protein composition in the blood and affect how the calculation behaves, which is one reason albumin and total protein context matter.
When the pattern seems unclear, revisit the basic metabolic panel, the albumin level, and the correction formula. A thorough review of lab values often explains why a seemingly simple blood test produces a complex result.
Frequently Asked Questions
How do you calculate the anion gap?
A standard anion gap calculation is sodium minus the combined total of chloride and bicarbonate: sodium − (chloride + bicarbonate). Some formulas also add potassium, but many routine calculations use the basic form from a routine electrolyte panel. The specific formula varies by laboratory and by the clinical assessment being used.
How is the effective anion gap calculated with albumin correction?
Begin by calculating the initial anion gap from the electrolyte panel. After that, use the albumin adjustment factor: corrected anion gap = measured anion gap + 2.5 × (4.0 − serum albumin). This correction helps adjust for albumin so low albumin does not obscure a true gap abnormality.
What is the role of albumin in anion gap correction?
Albumin is a major negatively charged protein in hyperchloremic acidosis NAGMA blood, so shifts in albumin alter the gap calculation. In reduced albumin, the measured gap may look falsely low or normal. Correcting for albumin improves the accuracy of acid-base analysis and the overall assessment of acid-base equilibrium.
What is the significance of a high anion gap?
A high anion gap usually suggests the presence of unmeasured acids and is commonly associated with metabolic acid buildup. Important causes include elevated lactic acid, ketone-related acidosis, impaired kidney function, and toxic alcohols. The result should always be interpreted alongside symptoms and other lab values.
Can metabolic acidosis occur with a normal anion gap?
Yes. A normal anion gap can occur even with metabolic acidosis, especially when bicarbonate falls and chloride rises in a way that preserves the calculation. This is one reason the result should be reviewed in the context of the entire metabolic panel, serum albumin, and the overall clinical picture.
In real-world use, an Anion Gap Calculator is most valuable when it supports a systematic review of the laboratory test: note the electrolytes, work out the raw gap, calculate anion gap with the standard formula, then corrected anion gap values in case albumin is low. That process offers a more accurate idea of whether the patient has a real acid-base disorder or a result that requires further investigation.