An anion gap calculator is a useful tool for transforming routine laboratory data into easier-to-understand blood gas interpretation. By bringing together values such as serum sodium, serum chloride, and serum bicarbonate, the calculator aids identify patterns that suggest metabolic acidosis and related acid-base disorder states. It is especially useful when paired with an arterial blood gas or venous blood gas, because the full picture depends on more than a single number.
Used well, the anion gap provides insight into unmeasured anions, possible toxic exposures, and broader electrolyte imbalance. It also enhances clinical interpretation when you are reviewing laboratory values in the context of a patient’s symptoms, pH, and base excess.
What the Anion Gap Measures
The anion gap is a estimated approximation of the discrepancy between observed cations and recorded anions in laboratory chemistry. In plain terms, it indicates the equilibrium between positively charged and negative particles in the blood, with electrolytes accounting for most of what is directly analyzed.
The primary inputs are serum sodium, serum chloride, and serum bicarbonate. Because sodium is the main measured cation and chloride plus bicarbonate are the primary measured anions, the gap aids identifying the presence of anion deficit from substances not routinely measured. These include lactate, ketones, sulfate, phosphate, and some toxins.
Clinically, the anion gap is not a diagnosis by itself. It is a indicator that assists narrow the differential diagnosis when reviewing an electrolyte imbalance or an acid-base problem. It is often most useful when paired with a buffer system assessment, pH, and bicarbonate level from blood gas testing.
Anion Gap Equation and Input Values
The standard formula for the anion gap reads:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some laboratories report potassium, but many do not. For that reason the reference range can vary by institution and by analyzer. An anion gap calculator should best match the method used by the lab that reported the values.
Although the formula is straightforward, the accuracy of the result depends on accurate laboratory values. Small variations in sodium, chloride, or bicarbonate can change the final answer, especially when the patient has a borderline result. In blood gas interpretation, bicarbonate may come from the blood gas analyzer or from the chemistry panel, and those values are not always identical.
https://anion-gap-help494.lucialpiazzale.com/anion-gap-calculator-and-interpretation-referenceAlbumin also matters because it is a major unmeasured anion. Since albumin contributes substantially to the normal gap, low albumin can make the calculated gap look smaller than it truly is. That is why many clinicians use an albumin-adjusted estimate when the patient has suspected hypoalbuminemia.
When blood gas values are available, the anion gap can be compared with pH and base excess to determine whether the patient has a pure metabolic process or a mixed disorder. This is where the calculator becomes more than just a math tool; it becomes part of the diagnostic workflow.
How to Understand a Typical vs Increased Anion Gap
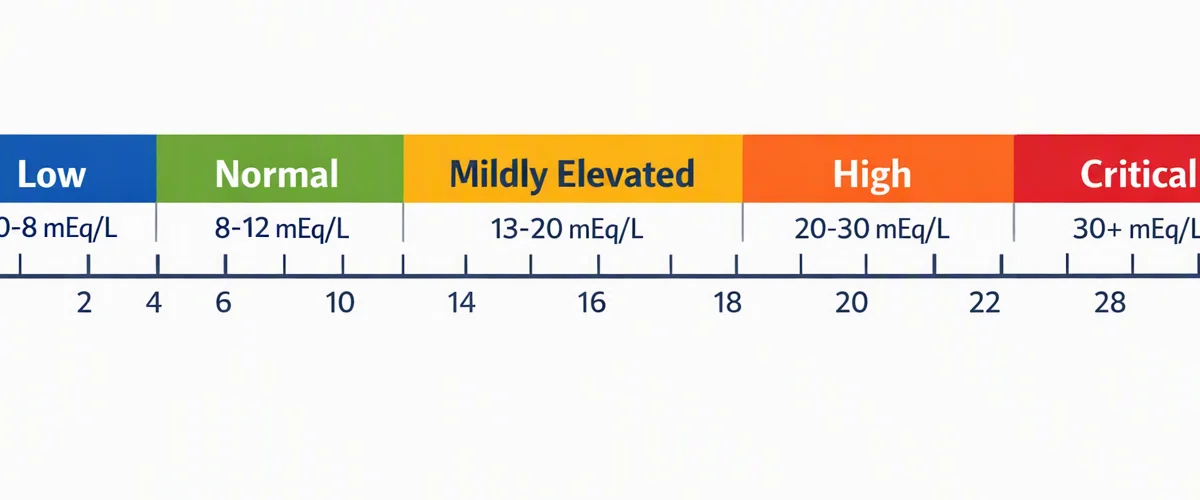
A typical anion gap commonly implies that any acid buildup present is being countered by a rise in chloride, which points toward normal anion gap metabolic acidosis. In this pattern, bicarbonate decreases, but chloride increases to support electroneutrality. This is often called hyperchloremic acidosis.
An increased anion gap suggests accumulation of unmeasured acids. That pattern is typical for high anion gap metabolic acidosis, where bicarbonate is consumed as the body neutralizes excess acid. The result is commonly a lower pH and a more marked disturbance in acid-base balance.
Evaluating the gap requires context. A patient may have a normal gap and still have significant illness, or an high gap with only mild pH change if there is respiratory compensation. The presence of a compensatory response can partially mask the severity of the metabolic problem.
When analyzing blood gas interpretation, check the whole pattern: pH, bicarbonate, base excess, and the calculated anion gap. A low pH with a low bicarbonate and elevated anion gap is very suggestive of metabolic acidosis. A near-normal pH does not exclude it if there is a concurrent respiratory or metabolic process.
Adjusting the Anion Gap for Albumin
Albumin correction is crucial because albumin is a negatively charged protein that helps form the normal gap. If albumin is low, the measured anion gap may downplay the degree of acid accumulation. This is common in patients with inflammation, malnutrition, liver disease, or critical illness, where hypoalbuminemia is present.
The albumin-corrected gap estimates what the gap would be if albumin were in the normal range. While formulas can vary slightly, the clinical principle is the same: lower albumin decreases the expected baseline gap, so the observed value should be adjusted upward to avoid missing an elevated state.
Why does this matter? Because a patient with a “normal” raw anion gap may actually have a clinically meaningful acid load once albumin is accounted for. This is especially helpful when the reference range appears normal but the patient has a clear metabolic picture on blood gas analysis.
Albumin adjustment improves diagnostic accuracy and helps prevent underrecognition of high gap disorders. It is one of the most practical ways to make an anion gap calculator more clinically useful.
Anion Gap in Blood Gas Interpretation
Interpreting blood gases is more complete when the anion gap is added to the evaluation. An arterial blood gas offers pH, bicarbonate, and often base excess, all of which help define the acid-base status. A venous blood gas can also be useful, especially when arterial sampling is not needed, and it often gives a reliable trend for pH and bicarbonate in the right clinical context.
The anion gap does not replace blood gas results; it augments them. For example, a low pH and low bicarbonate suggest metabolic acidosis, but the anion gap tells you whether the cause is likely accumulation of unmeasured acids or depletion of bicarbonate with chloride retention. That distinction directs the next step in the diagnostic workflow.
Base excess is another helpful piece. A negative base excess supports a metabolic acid load, while the degree of abnormality can help estimate the severity of the disturbance. Together, pH, base excess, and the anion gap strengthen clinical interpretation of the overall acid-base disorder.
In practice, blood gas interpretation often follows a sequence: check pH, determine whether the problem is metabolic or respiratory, assess bicarbonate and base excess, then use the anion gap to classify the metabolic disturbance. This layered approach is essential for identifying mixed disorders and avoiding a missed diagnosis.
Typical Causes of Increased Anion Gap Metabolic Acidosis
High anion gap metabolic acidosis occurs when acids accumulate at a faster rate than the body can buffer or remove them. Multiple likely causes should be reviewed during clinical assessment.
- Lactic acidosis: commonly linked to tissue hypoperfusion, sepsis, seizures, or severe physiologic stress. Lactate elevation reflects impaired oxygen delivery or altered metabolism. Acid buildup from ketones: may develop with diabetic ketoacidosis, starvation, or alcohol-related ketone production. Ketone production adds unmeasured acids that increase the gap. Renal insufficiency: reduced acid excretion can lead to retention of sulfate, phosphate, and other acids, especially when kidney impairment is significant. Toxic alcohol ingestion: methanol, ethylene glycol, and related substances can produce severe metabolic acidosis, often with an osmolar gap as well. Toxic ingestion should be considered urgently when the history suggests it.
These conditions often present with altered mental status, tachypnea, or signs of poor perfusion, but the lab pattern is what often makes the diagnosis visible. The anion gap calculator helps detect the biochemical signature early, even before the full cause is obvious.
Often, a rising gap is the first sign that something serious is developing. That is why anion gap assessment is key to metabolic acidosis workup and emergency acid-base analysis.
Typical Causes of Normal Anion Gap Metabolic Acidosis
Normal anion gap metabolic acidosis is usually caused by bicarbonate loss or decreased bicarbonate replacement, with chloride increasing to keep electrical balance. This is why it is also called hyperchloremic acidosis.
- Diarrhea: loss of bicarbonate through the gut is a classic cause and may be clinically obvious. Renal tubular acidosis: defective renal acid handling or bicarbonate conservation leads to persistent acidosis despite preserved or near-preserved filtration in some cases. Bicarbonate loss: can occur through gastrointestinal losses, renal losses, or certain medications and procedures. Hyperchloremic acidosis: often reflects the compensatory chloride rise that accompanies bicarbonate depletion.
Even when the anion gap is normal, the patient may still have a important acid-base disorder. A normal gap does not mean the blood gas interpretation is reassuring; it simply points to a different mechanism. This is why correlating the electrolyte panel with pH and bicarbonate is so important.
Some cases are mixed, with both elevated and normal gap components present at the same time. In those situations, the anion gap calculator gives only part of the answer, and additional analysis is needed.
Using the Anion Gap Calculator Clinically
In clinical practice, the anion gap calculator is particularly helpful when it is part of a structured review of laboratory values. Start with the electrolyte panel, confirm sodium, chloride, and bicarbonate, then compare the result with blood gas findings. This creates a more reliable diagnostic workflow than looking at any single number in isolation.
The calculator can support clinical decision-making in several ways. It can help confirm metabolic acidosis, distinguish high-gap from normal-gap causes, reveal hidden acid accumulation in hypoalbuminemia, and prompt urgent evaluation for toxic ingestion or renal impairment. It can also guide whether additional tests are needed, such as lactate, ketones, or repeat chemistry studies.
With optimal accuracy, use the calculator using the matching analytical platform and lab method that generated the patient’s chemistry results. This maintains the interpretation aligned with the local reference range and improves consistency across repeated measurements.
The most useful approach is to view the anion gap as a element of integrated acid-base analysis, not as a stand-alone answer. When combined with pH, base excess, and albumin, it acts as a useful decision support tool.
Constraints and Typical Calculation Pitfalls
As with any lab-based tool, an anion gap calculator has limitations. One of the biggest issues is measurement error. Small inaccuracies in sodium, chloride, or bicarbonate can change the result enough to move a patient from one category to another, especially when the gap is borderline.
The albumin effect is a further major pitfall. If hypoalbuminemia is not considered, a true high-gap state may appear deceptively normal. That is why albumin adjustment should be included in any thorough interpretation when albumin is low or thought to be low.
Another common issue is the delta gap. In mixed acid-base disorders, comparing the rise in anion gap to the fall in bicarbonate can show whether an additional metabolic process is present. A delta gap can help detect concurrent metabolic alkalosis or a combined high-gap and normal-gap acidosis.
Finally, do not forget that lab reference range values differ across institutions and analyzers. A result considered normal in one setting may be slightly abnormal in another. Interpretation should always be connected to the laboratory’s own standards and the patient’s clinical picture.
These pitfalls matter because they can alter the interpretation of blood gas results. Careful review helps reduce missed diagnoses and enhances diagnostic accuracy in acid-base analysis.
Common Questions
What is an anion gap calculator used for?
An anion gap calculator is used to calculate the gap between measured cations and anions in the blood. It helps with blood gas interpretation, detects possible metabolic acidosis, and assists with evaluation of electrolyte and acid-base disorders.
How do you calculate the anion gap from blood gas results?
Apply the anion gap formula: sodium minus chloride, then plus bicarbonate. If the bicarbonate comes from an arterial blood gas or venous blood gas, ensure it is the same value being used consistently. Then review the result with pH, base excess, and the clinical picture.
Why does albumin affect the anion gap?
Albumin is a major unmeasured anion, so low albumin reduces the expected gap. With hypoalbuminemia, the measured value may look normal even when acid is accumulating. That is why albumin correction and the corrected anion gap are significant.
What causes a high anion gap in metabolic acidosis?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. These conditions contribute unmeasured acids to the blood and reduce bicarbonate as buffering occurs.
Can a normal anion gap still indicate a serious acid-base problem?
Yes. A normal anion gap metabolic acidosis can still be clinically significant, especially when caused by diarrhea, renal tubular acidosis, or bicarbonate loss. Blood gas interpretation should also consider pH, base excess, and other laboratory values because a normal gap does not exclude a serious disorder.