An anion gap calculator is a helpful tool for lab interpretation that helps interpret electrolyte patterns in a serum chemistry panel. It is not a diagnosis by itself, but it can offer a important diagnostic clue when reviewing blood chemistry results and evaluating acid-base balance. By comparing the measured serum sodium, serum chloride, and serum bicarbonate, the calculator estimates the anion gap, which can help identify an electrolyte imbalance or a broader acid-base disorder.
Understanding the anion gap is especially helpful when reviewing an electrolyte panel, a basic metabolic panel, or a comprehensive metabolic panel. These tests are commonly used in medical screening, patient evaluation, and diagnostic workup. The result can guide clinical decision support, but it should always be interpreted alongside symptoms, history, and other supportive findings.
What specifically the Anion Gap Measures
The anion gap reflects the gap between the main positively charged and negatively charged particles in the blood, using standard serum electrolytes. Put simply, it contrasts the amount of sodium with the combined amount of chloride and bicarbonate. As routine lab tests do not directly assess every charged particle in the blood, the anion gap approximates the amount of unmeasured anions.
This makes anion gap a useful marker in lab interpretation. If the gap is high, it may indicate that acids or other unmeasured substances are accumulating in the body. If the gap is low, it may reflect changes in albumin, lab variation, or in some cases another underlying issue. In clinical practice, this result often functions as a diagnostic clue rather than a final answer.
The anion gap is most often evaluated when a provider is looking for a metabolic derangement, especially if there is concern for metabolic acidosis. It can help narrow the differential diagnosis and support a more targeted evaluation.
Anion Gap Formula and Calculation
The standard anion gap formula is:
Anion gap = plasma sodium - (plasma chloride + serum bicarbonate)
In general use, this shows the calculator takes the plasma sodium, subtracts the total of plasma chloride and serum bicarbonate, and gives an anion gap value. Some calculators may also support slightly different formulas depending on whether potassium is included, but the standard version does not include potassium.
This calculation is commonly done from lab values in a basic metabolic panel or comprehensive metabolic panel. Because the formula depends on the blood chemistry values reported by the laboratory, even small differences in testing methods or reference standards can affect the result. That is why checking the particular reference range used by the lab matters.
The anion gap calculation is a valuable form of clinical decision support because it helps identify patterns that might not be obvious from the individual numbers alone. For example, a low bicarbonate with a normal or elevated gap suggests different possibilities than a low bicarbonate with a normal gap.
How to Understand a Standard, Increased, or Decreased Anion Gap
A normal result usually means the measured electrolytes are in a state consistent with normal acid base balance. That said, a normal result does not always exclude disease. It simply suggests the result does not strongly indicate excess unmeasured acids.
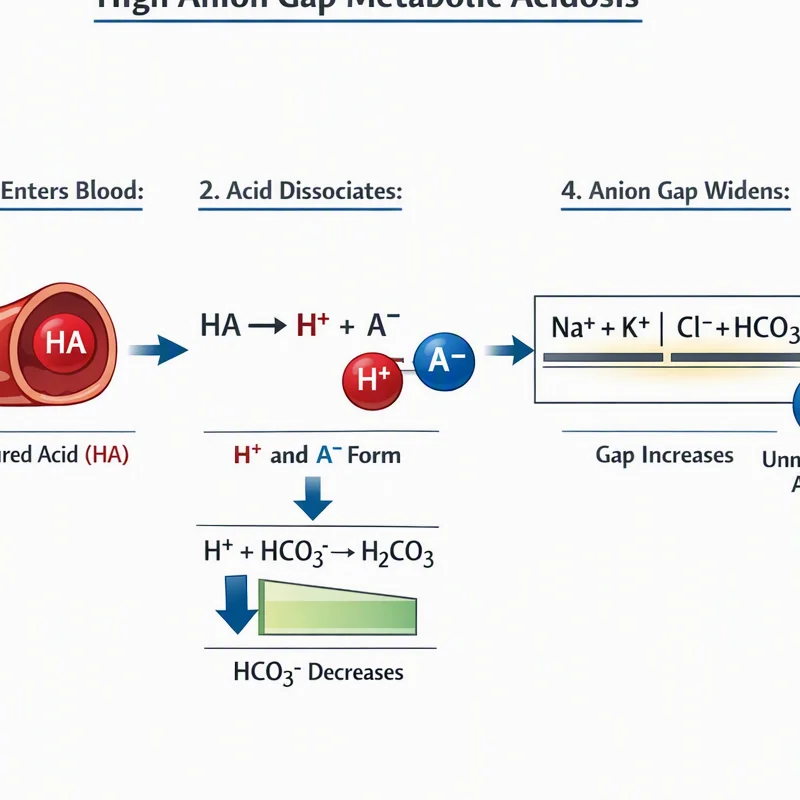
A increased anion gap metabolic acidosis is a major finding because it often shows that acids are building up in the body. This can happen when the body produces too much acid, cannot clear acid effectively, or is exposed to a substance that creates acid. A high gap is often one of the main patterns in an acid-base disorder and can be a key diagnostic clue during patient evaluation.
A reduced anion gap is uncommon. It may MUDPILES mnemonic be caused by laboratory variation, changes in proteins, or certain medical conditions. A key factor to consider is albumin, since this protein carries negative charge in the blood and contributes to the gap. When albumin is low, the anion gap may appear decreased than expected even if the overall clinical picture implies otherwise.
Understanding the result requires context. The same anion gap value can have quite different meaning depending on the presence of symptoms, kidney function, medication use, and other lab abnormalities. That is why the result should be viewed as part of an broader interpretation guide rather than as a standalone diagnosis.
Frequent Reasons of an Irregular Anion Gap
Various conditions can cause an abnormal anion gap. Certain ones are urgent and demand rapid review, while others are more long-term or related to other lab findings.
- Lactic acidosis can elevate the gap when lactic acid accumulates, often during poor tissue oxygenation, severe illness, or shock. Ketoacidosis, including diabetic ketoacidosis or starvation-related ketosis, can also produce a high gap because ketones are unmeasured anions. Renal failure may impair the body’s ability to remove acids, leading to accumulation of unmeasured acids and a high gap. Toxic alcohol ingestion is another important source of a high gap and can be connected with serious metabolic derangement.
These causes are part of the differential diagnosis when a provider notes an abnormal lab result. The pattern does not prove a specific condition on its own, but it can help guide the diagnostic workup. For example, high-gap acidosis may prompt evaluation for ketones, lactate, kidney function, or toxin exposure.
Not all acid-base disorders increase the gap. In normal anion gap metabolic acidosis, bicarbonate is lost or reduced, but the gap stays about the same because chloride often rises to compensate. This is sometimes described as a chloride shift, where chloride replaces lost bicarbonate to preserve electrical balance.
That distinction is clinically important. A normal gap and a high gap point to different mechanisms, so the calculator helps structure the interpretation of blood chemistry results.
Adjusting the Anion Gap for Albumin
Low albumin, meaning low albumin, can cause the measured anion gap appear lower than it truly is. Since albumin is one of the key negatively charged proteins in the blood, it affects the balance of charged particles and the final gap value. This is why correction for albumin is often recommended when reviewing results in hospitalized or ill patients.
A albumin-adjusted anion gap is computed by raising the measured value upward when albumin is low. The exact correction method can vary by institution, but the basic idea is the same: if albumin is reduced, the anion gap should be read with caution because the raw number may underestimate the presence of unmeasured acids.
The reason this counts comes down to albumin binding and charge balance. Albumin normally contributes negative charge, so when levels fall, the body may appear to have fewer unmeasured anions than it actually does. Correcting for this can improve acid-base assessment and lower the risk of missing a clinically meaningful high gap.
Albumin correction is especially helpful when assessing patients with severe illness, inflammation, liver disease, or poor nutrition. In those settings, an apparently normal anion gap may conceal a true acid-base disorder. This is one reason the corrected value is often more informative than the unadjusted number alone.
Using an Anion Gap Calculator Step by Step
An anion gap calculator is simple to use, but accurate input matters. The tool is only as helpful as the lab values entered into it, so it is crucial to use the precise numbers reported by the laboratory.
- Find the serum sodium, serum chloride, and serum bicarbonate from the lab report. Type those numbers into the calculator input fields. See if the calculator includes an albumin adjustment option. Review the calculated anion gap value and check it with the stated reference range. Interpret result interpretation in the context of symptoms, history, and other labs.
If the calculator provides a reference range, compare the result to that range rather than assuming one universal cutoff. Different laboratories may use slightly different methods or reporting standards. That means a result that is near the limit in one setting may be considered within range in another.
For best use, the calculator should be seen as a lab interpretation aid, not a replacement for professional judgment. It can support pattern recognition, but it cannot diagnose the cause of an abnormal result by itself. A careful clinician will combine the anion gap with the patient’s condition, other blood chemistry markers, and any relevant symptoms.
In practice, a calculator can be a quick way to identify whether the data suggest an acid-base disorder, whether albumin correction is needed, and whether the pattern should prompt a more detailed diagnostic workup. That makes it a practical tool for clinical decision support and patient evaluation.
When to Pursue Clinical Evaluation
An unexpected anion gap should be brought to a medical provider, especially when it occurs with concerning symptoms. These may include shortness of breath, confusion, vomiting, severe fatigue, dehydration, or signs of worsening illness. In the appropriate context, these symptoms can suggest metabolic acidosis or a separate serious condition.
Emergency care may be necessary if there are severe symptoms, altered mental status, breathing changes, or suspected toxin exposure. A high gap in combination with illness can suggest a potentially serious metabolic derangement that should not be ignored. If toxic alcohol ingestion is possible, prompt evaluation is particularly important.
Even a low or normal result may warrant additional review if the patient has persistent symptoms or other abnormal findings. The calculator is helpful for screening and interpretation, but it is not a substitute for medical advice. A provider can determine whether the result fits the larger clinical picture and whether additional testing is needed.
In short, the anion gap is one part of a broader lab interpretation process. It helps highlight patterns, but the real value comes from connecting those patterns to the patient’s overall presentation.
Common Questions
What is an anion gap calculator used for?
An anion gap calculator is used for interpreting lab results and clinical anion gap clinical significance decision support. It helps calculate the anion gap from serum sodium, serum chloride, and serum bicarbonate, which can reveal clues about acid base balance, electrolyte imbalance, and possible metabolic acidosis.
What is the normal anion gap range in adults?
The normal range can vary by testing facility and by the formula used, so the best answer is to check the specific reference range listed with the lab report. Some labs use a tighter or wider range depending on their methods and whether albumin correction is considered.
Why would the anion gap high in metabolic acidosis?
A raised anion gap in metabolic acidosis usually means there are higher levels of unmeasured anions in the blood, such as lactate or ketones. This picture is often seen in high anion gap metabolic acidosis and can be due to lactic acidosis, ketoacidosis, renal failure, or toxic alcohol ingestion.
How do you correct the anion gap for low albumin?
To adjust the anion gap for low albumin, clinicians use an albumin correction formula that modifies the measured value upward when hypoalbuminemia is present. Because albumin normally contributes negative charge through protein binding, a low level can make the raw result look falsely low. The corrected anion gap provides a more accurate picture for acid-base interpretation.
Can a low anion gap be a sign of a serious problem?
Absolutely, a low anion gap can occasionally be associated with a serious problem, although it is often due to lab variation or low albumin. It should be reviewed in context, especially if there are other abnormal lab results or symptoms. A medical provider can determine whether it reflects a benign finding or needs a diagnostic workup.